GI Endoscopy · 6 min read
Sudeck's Point in 2026: Rectosigmoid Watershed After IMA Ligation
The rectosigmoid watershed is a surgical problem more than a hypotensive one. Griffith's point at the splenic flexure is the usual map for low-flow colon ischemia.
Sudeck's point is the junction of the last sigmoid artery and the superior rectal artery, at the rectosigmoid. A macroscopic anastomosis is present in most cadavers, but the vessel is about 2 mm and sometimes absent. That is why IMA ligation during aortic or rectal surgery can leave the distal stump hungry. It is not the usual site of hypotensive colon ischemia. That is Griffith's point.
Experienced teaching points
Clinical Pearls
- Sudeck's point is rectosigmoid. Griffith's point is the splenic flexure. Mixing them is how the wrong artery gets blamed.
- van Tonder's cadaver series: a macroscopic last-sigmoid to superior-rectal anastomosis was missing in 4.7%. When present, mean diameter was 1.9 mm. Present is not the same as adequate.
- Hypotensive colon ischemia still prefers the splenic flexure. Rectosigmoid ischemia after AAA repair or high IMA ligation is the Sudeck story.
- The middle and inferior rectal arteries from the iliacs often spare the low rectum. A dusky anastomosis just above the pelvic floor is the leftover risk.
- If the colon looks ischemic after IMA sacrifice, this anatomy page is the map. Management lives on the colon ischemia page.
Clinical Bottom Line
| Question | 2026 practical answer |
|---|---|
| Where is it? | Origin of the last sigmoid branch of the IMA, and its anastomosis (when present) with the superior rectal artery, at the rectosigmoid junction. |
| Is the anastomosis real? | Usually. van Tonder: absent in 3 of 64 cadavers (4.7%). Mean caliber 1.9 mm. Small enough that "present" does not mean the caudal stump will live. |
| When does it matter? | High IMA ligation in rectal cancer, open AAA repair, ruptured EVAR with IMA coverage, and any pelvic dissection that takes sigmoid vessels. Confirm pulsatile flow at the proximal anastomotic cut edge before you staple. |
| When does it not? | Typical hypotensive left-sided colon ischemia. That watershed is Griffith's point at the splenic flexure, where Drummond is often tenuous. |
| Clinical page | Diagnosis, colonoscopy, IRCI, and surgery: colon ischemia. AMI vs CI: the differentiator. |
Where is Sudeck's point?
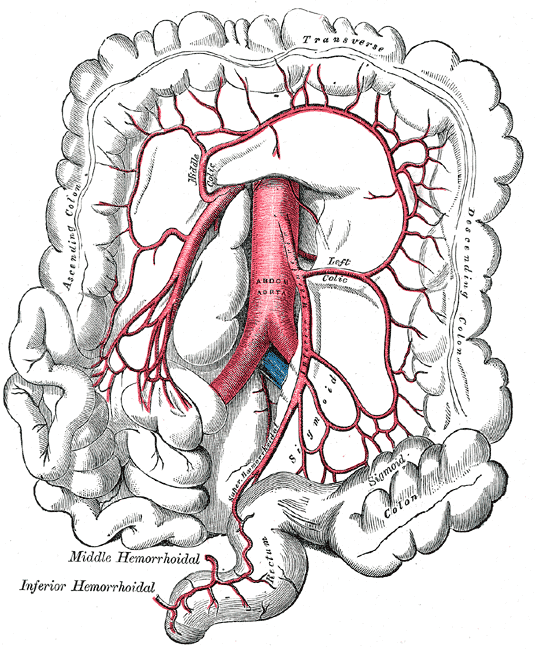
Paul Sudeck described a critical point at the rectosigmoid where the last sigmoid artery meets the superior rectal artery, both IMA branches. Distal to that junction the rectum still has iliac collaterals (middle and inferior rectal). Proximal to it, the sigmoid depends on IMA flow and on whatever Drummond and the last-sigmoid anastomosis will give it.
Gray's plate 537 is the picture to hold in your head: IMA off the aorta, left colic, sigmoid arteries, then the superior rectal diving into the pelvis. Sudeck's point is not labeled on the 1918 plate. It is the last junction before the superior rectal becomes a solo act.
Is it still a true watershed?
Modern dissection softened the mythology without retiring the landmark. van Tonder, Boon, Becker, and van Schoor dissected 64 cadavers without prior rectosigmoid surgery. A macroscopic anastomosis between the last sigmoid branch and the superior rectal artery was missing in 4.7%. When present, mean diameter was 1.9 mm (SD 0.5). Distance from IMA origin to Sudeck's point averaged 55.5 mm, which is enough room to ligate the IMA proximal to the point if you are trying to preserve that last sigmoid takeoff.
So the older sentence "there is no collateral at Sudeck's point" is too clean. The honest sentence is: the collateral is usually there, it is small, and it may not feed a stapled anastomosis once the IMA is gone and the patient is vasoconstricted in a recovery room.
Yamazaki's clinical reports of ischemic stricture below Sudeck's point after sigmoidectomy are the practical remainder of the debate. Anatomy is not a promise. Perfusion of the cut edge is.
When does it matter in the OR?
ACG 2015 already lists IMA sacrifice (AAA repair and other abdominal operations) as a reason to think of colon ischemia when the postoperative story fits. Open aneurysm repair and ruptured EVAR are the classic setups. High IMA ligation for rectal cancer is the elective version: you take the IMA at the aorta for nodes and you are betting that Drummond plus iliacs will keep the descending colon and the rectal stump alive.
Before the anastomosis, look at the cut edge. Pulsatile bleeding, a pink mucosa, and a Doppler or ICG signal beat a textbook drawing. If the proximal colon is dusky, more proximal resection is cheaper than a leak. The low rectum often survives on iliac flow even when the sigmoid does not. That mismatch is how you get an ischemic anastomosis a few centimeters above the pelvic floor with a viable dentate line.
On the later colonoscopy, a segmental dusky or ulcerated rectosigmoid with a spared low rectum, in a patient whose IMA was ligated last week, is Sudeck until proven otherwise. Management is the colon ischemia page, not another anatomy lecture.
How does it differ from Griffith's point?
Griffith's point is the splenic flexure, the SMA-IMA watershed, where the marginal artery of Drummond is often the weak link. That is the map for hypotensive, nonocclusive colon ischemia in a medical patient. Sudeck's point is IMA territory talking to itself at the rectosigmoid. Mixing the names makes you look for the wrong segment and call the wrong surgeon.
Drummond still matters here: if the marginal arcade is robust, left-colon flow can arrive from the middle colic even after IMA ligation, and Sudeck's tiny anastomosis is less of a veto. If Drummond is incomplete at the flexure, the left colon is already on a thin wire before you ever reach the pelvis. Read Griffith's point and Drummond with this page, not instead of it.
Selected references
- van Tonder JJ, Boon JM, Becker JHR, van Schoor AN. Anatomical considerations on Sudeck's critical point and its relevance to colorectal surgery. Clin Anat. 2007;20:424-427.
- Brandt LJ, Feuerstadt P, Longstreth GF, Boley SJ. ACG Clinical Guideline: Colon Ischemia (CI). Am J Gastroenterol. 2015;110:18-44.
- Yamazaki T, Shirai Y, Sakai Y, Hatakeyama K. Ischemic stricture of the rectosigmoid colon caused by division of the superior rectal artery below Sudeck's point during sigmoidectomy: report of a case. Surg Today. 1997;27:254-256.
- Perry RJ, Martin MJ, Eckert MJ, Sohn VY, et al. Colonic ischemia complicating open vs endovascular abdominal aortic aneurysm repair. J Vasc Surg. 2008;48:272-277.
- Colon ischemia clinical page and Griffith's point.
Last reviewed September 20, 2026. Written for clinicians who keep mixing Sudeck's point with Griffith's point, and for the endoscopist looking at a dusky anastomosis after IMA ligation.
Topics
For your teaching file
Save this article as a PDF
Drop your email and we'll open a print-ready version you can save as a PDF — and you'll start getting our weekly GI endoscopy newsletter.