GI Endoscopy · 7 min read
Couinaud Segments: Portal Pedicle in the Center, Hepatic Veins at the Borders
Cantlie's line is the middle hepatic vein. Number from the caudate. Do not call segment III left medial.
Couinaud split the liver into eight functionally independent portal segments. Each has its own portal triad. The three hepatic veins sit at the borders, not in the middle of the piece you are naming. Brisbane 2000 (Strasberg, PMID 16258801) is how you say the resection. The table that used to live on this URL called II/III 'left lateral / left medial.' That is wrong. II and III are the left lateral section. IV is the left medial section.
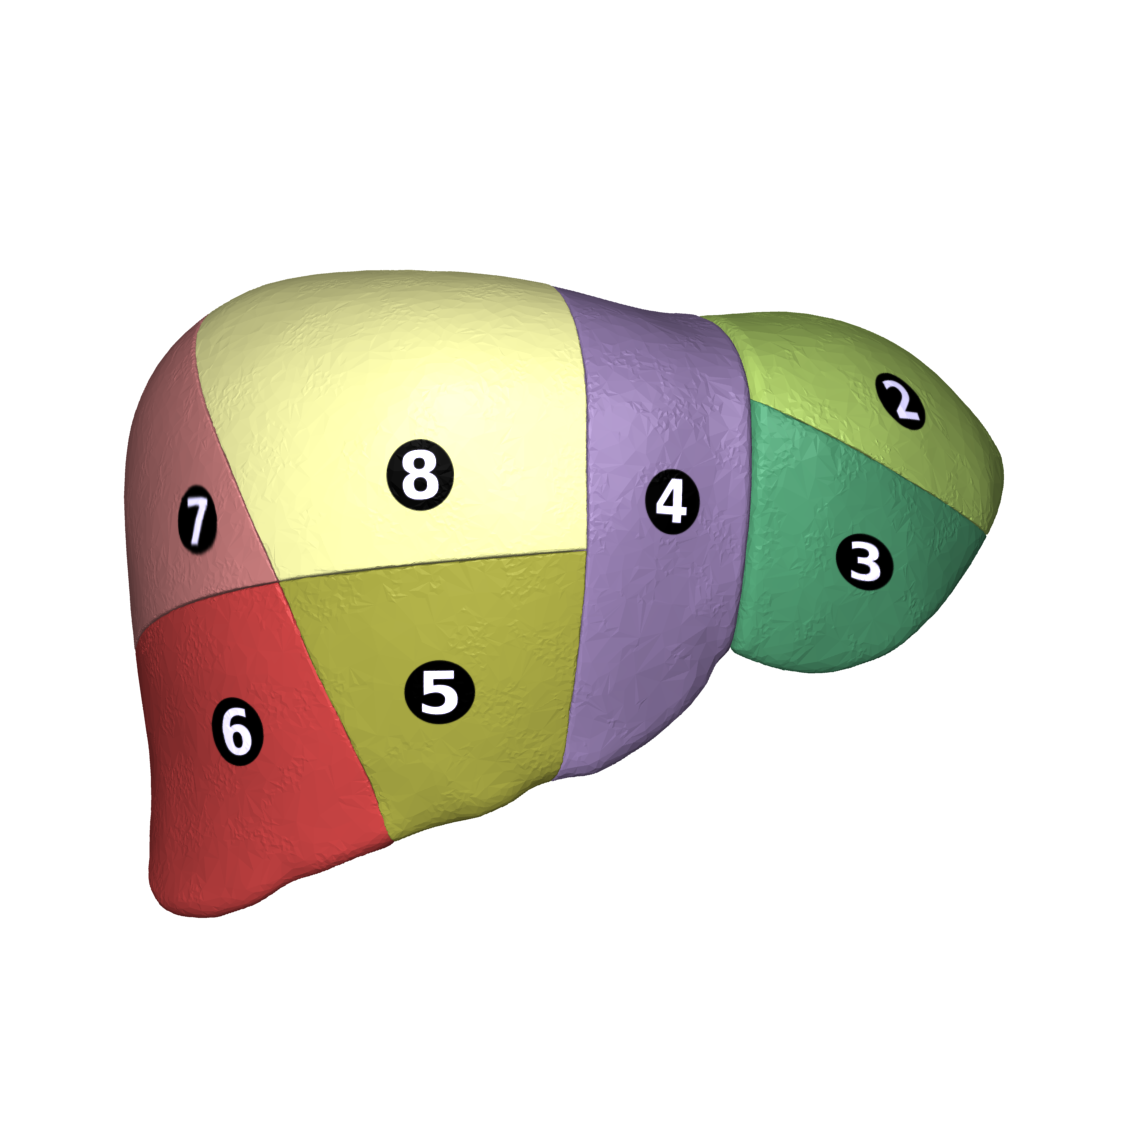
Experienced teaching points
Clinical Pearls
- Portal pedicle in the center of the segment. Hepatic veins at the scissurae. If you reverse that, the map is useless in the OR.
- II and III: left of the falciform (left lateral section). IV: between falciform and the middle hepatic vein (left medial). Do not swap III and IV.
- Cantlie's line runs from gallbladder fossa to IVC. That is the middle hepatic vein and the right/left hemiliver split.
- Segment I (caudate) takes portal flow from both sides and drains straight to the IVC. It is not 'part of IV.'
- Variceal TIPS planning is a different page: preemptive TIPS. ACLF grading: CLIF-C.
Clinical Bottom Line
| Piece | What it actually is |
|---|---|
| I | Caudate. Portal from left and right. Veins straight to IVC. Independent of the three main hepatic veins (Bismuth 1982, PMID 7090393). |
| II and III | Left lateral section, left of the falciform. II is superior, III inferior. Both are lateral. Neither is medial. |
| IV (IVa / IVb) | Left medial section, between falciform and middle hepatic vein. IVa superior, IVb inferior toward the gallbladder. |
| V and VIII | Right anterior section. V inferior, VIII superior. Between middle and right hepatic veins. |
| VI and VII | Right posterior section. VI inferior, VII superior. Right of the right hepatic vein. |
| Resection language | Brisbane 2000 (PMID 16258801): first-order hemihepatectomy, second-order sectionectomy, third-order segmentectomy. "Right hepatectomy" is V-VIII, not "right lobectomy." |
Why is III not left medial?
The falciform and the ligamentum teres mark the left portal fissure. Everything to the left of that fissure on the anterior surface is the left lateral section: II above, III below. Segment IV sits to the right of the falciform and to the left of Cantlie's line. Calling III "left medial" mixes a Couinaud number with a Brisbane section and then puts it on the wrong side of the ligament. Left lateral sectionectomy is II+III. Left medial sectionectomy is IV. Those are different operations.
Couinaud (1957) built the map from portal casts. Bismuth (PMID 7090393) made it usable in the OR: three hepatic veins as scissurae, portal pedicles as the cores. Brisbane 2000 (Strasberg, PMID 16258801) stopped people saying "left lobectomy" when they meant II+III or II-IV. First-order: right hepatectomy V-VIII, left hepatectomy II-IV. Second-order: right anterior V+VIII, right posterior VI+VII, left lateral II+III, left medial IV. Extended right (right trisectionectomy) adds IV. Extended left adds V+VIII.
What does a GI need this for?
To read the note. To target a drain or an ablation. To hear "segment VII metastasis" and know it is posterior-superior right, not "somewhere in the right lobe." Hilar cholangiocarcinoma (Bismuth-Corlette) is named off this same split: the confluence versus left and right sectoral ducts. Living-donor and RFA planning fail when portal variants are ignored (right anterior from left portal is the classic trap). Cirrhosis distorts the map. Volumetry beats a textbook drawing once the left lobe has hypertrophied and the right has shrunk.
Do not restage TIPS insertion, banding, or ACLF here.
Selected references
- Strasberg SM. Nomenclature of hepatic anatomy and resections: a review of the Brisbane 2000 system. J Hepatobiliary Pancreat Surg. 2005;12:351-355.
- Bismuth H. Surgical anatomy and anatomical surgery of the liver. World J Surg. 1982;6:3-9.
- Couinaud C. Le foie: etudes anatomiques et chirurgicales. Paris: Masson; 1957.
Last reviewed September 20, 2026. Written for clinicians reading a surgical note, targeting an abscess or RFA, or translating a Bismuth-Corlette hilar map into Couinaud segments.
For your teaching file
Save this article as a PDF
Drop your email and we'll open a print-ready version you can save as a PDF — and you'll start getting our weekly GI endoscopy newsletter.